The Landlord’s Algorithm
Clinical AI is becoming the cognitive infrastructure of Canadian medicine. Who owns it?
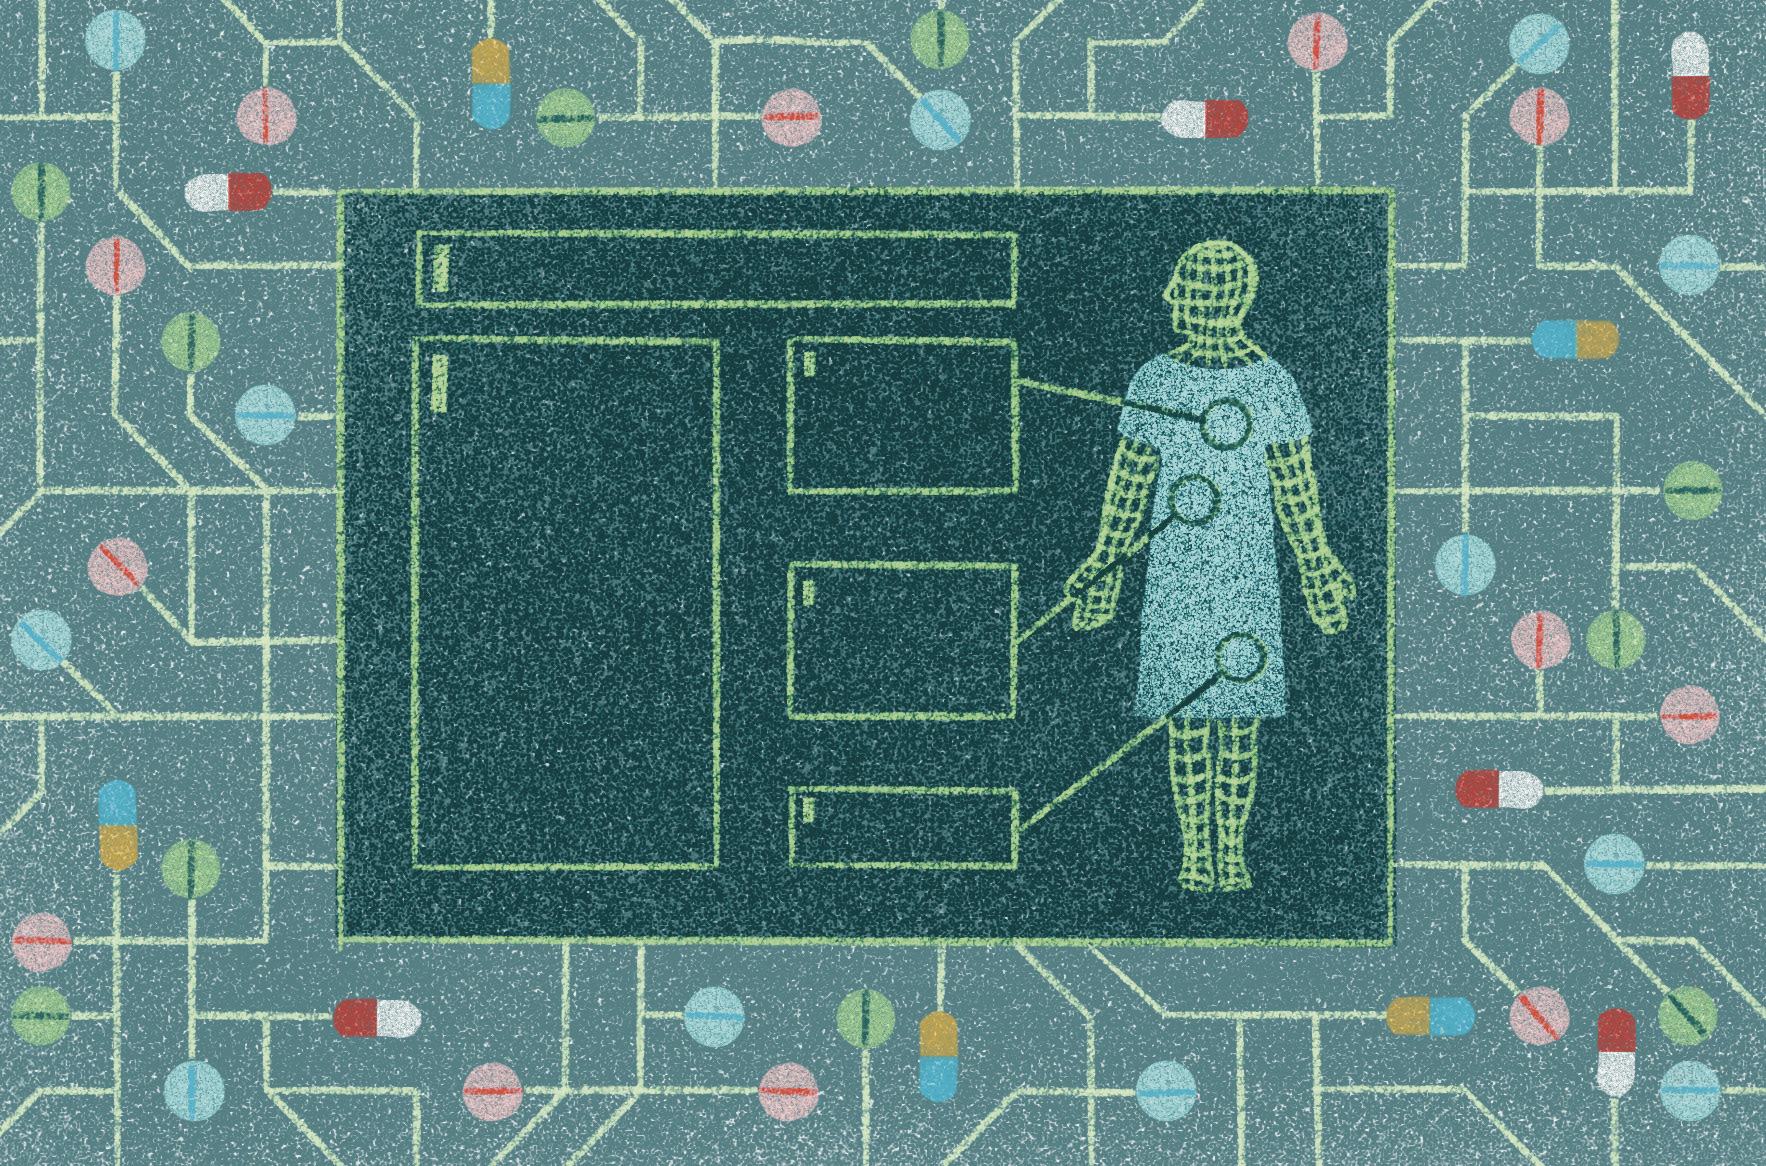
A clinical AI tool usually arrives as a contract before it arrives as a clinical reality. First there are demonstrations, procurement documents, security reviews, and promises of efficiency. Then one day it sits inside the chart. A risk score appears. A note is summarized. A triage recommendation is made. The physician experiences it as clinical support; the patient experiences it as care. But underneath that moment is an agreement about property: who owns the model, who can inspect it, where the data go, and what happens when dependence sets in.
The most consequential decision your hospital will make about AI may not look like a clinical decision at all. It may look like procurement. The decision may include superficial risk analysis, some clinical consultation, literature review, or even a thin, rushed patient safety assessment in order to give the impression of legitimacy but, ultimately, it may be made like any other technology procurement decision, under the guise of budgetary constraints. Often very quickly, we may welcome one or another of a handful of dominant American tech companies into our hospitals, give them the keys and our data, and surrender sovereignty, workforce skill, and future independence for apparent short-term convenience.
We have already worked out what we believe about privately owned healthcare infrastructure. Why should AI be any different?